
The right AI scribe for a psychiatry practice is the one that writes the mental status exam and the risk assessment as discrete sections, codes the E&M visit plus the psychotherapy add-on from what was actually said, keeps clinical reasoning off the patient portal, and lands the note in your EHR's fields — not a generic SOAP note you copy-paste. Judged that way, the answer depends on the practice:
- Independent psychiatry or PMHNP practice on eClinicalWorks, athenaOne, AdvancedMD, OptiMantra or DrChrono — DeepCura, because the note is built to your template and written into those systems' fields (details, with the exact field routing, below).
- Documentation-only depth for behavioral health, part-time volume — JotPsych, whose sections and pricing are built around psychiatry alone.
- The least setup on a browser-based EHR DeepCura does not write into (SimplePractice, TherapyNotes, Valant, Osmind) — Freed AI's browser push is a fair choice.
- Multilingual sessions or a free tier to try first — Heidi Health.
- Health-system psychiatry on Epic or Cerner with enterprise procurement — Nuance DAX / Dragon Copilot, or Suki for voice-command charting.
- Therapy-only practices — see the therapists and therapy notes guides instead; this page is about psychiatric prescribers.
DeepCura publishes this guide and is one of the tools discussed. Competitors are recommended where they fit better, and prices for every vendor were verified on the dates shown in the tables. Product screenshots are real captures — from a demo account with synthetic patients, or from public pages, as each caption states. Product-workflow and EHR-routing statements are taken from the shipping product and its code, with the file paths noted where they matter; no independent clinician reviewed this page.
What a psychiatric note demands that a primary-care scribe does not
Most ambient scribes were built for the primary-care encounter: chief complaint, HPI, exam, assessment and plan. A psychiatric visit is structured differently, and the differences are exactly where general-purpose tools break down.
The mental status exam as discrete fields
The MSE is psychiatry's physical exam — appearance, behavior, speech, mood (patient-reported), affect (clinician-observed), thought process, thought content, perception, cognition, insight and judgment. A general-purpose scribe tends to write "patient appears anxious." A psychiatric note needs the clinical distinctions the scribe should have heard: constricted versus blunted affect, pressured versus tangential speech, passive versus active ideation. Whether those land as labeled fields or get buried in narrative decides whether the note is chartable, auditable and useful at the next visit.
Risk assessment that is prominent, not buried
Suicidal ideation (active vs. passive, plan, intent, access to means), homicidal ideation, self-injurious behavior, protective factors, and the validated instruments — C-SSRS, PHQ-9, GAD-7 — belong in a dedicated section near the top of the assessment. A scribe that scatters this across the HPI creates clinical and legal exposure.
Med-management visits: fifteen minutes, five documentation duties
Medication reconciliation, side-effect screening, the rationale for each dose change, interaction considerations, and a risk–benefit statement — in a 15–20 minute slot. Controlled-substance visits add the PDMP check, informed consent and refill interval. Templates that prompt for these from the conversation are worth more than "unlimited notes."
Therapy inside a psychiatry visit: the add-on problem
When an E&M visit includes psychotherapy, the add-on codes (90833 / 90836 / 90838) require the therapy time and content documented separately from the medical management. Notes that blend the two make the add-on hard to defend.
Portal-visible versus provider-only
Under the 21st Century Cures Act information-blocking rules, most notes are visible to the patient in the portal. Psychiatric reasoning — a differential you are still weighing, weight and calorie detail for an eating-disorder patient, a step-therapy justification written for a payer — often should not be. Some EHRs give you a provider-only field; eClinicalWorks does (its internal Clinical Notes versus the portal-visible Treatment notes), and the scribe has to know which is which. We come back to that below.
How the note gets built for your practice (there is no template library, on purpose)
Ask a vendor "do you have psychiatry templates?" and you usually get a list. DeepCura's honest answer is different: there is no fixed library of pre-built psychiatry templates. Templates are built for your account, three ways.
On the setup call. The onboarding agent, Emily, builds a specialty template during onboarding — it is a required step, not an upsell. The template generator is instructed to "use specialty-specific section names and clinical terminology (not generic HPI/Assessment/Plan)", to "include Medical Decision Making (MDM) elements" and "risk stratification language", and to "support ICD-10 specificity" — while being forbidden from pre-populating any clinical content, so that an instruction is designed not to bleed a finding into a note where it was not discussed. In practice a psychiatry template comes out with an interval history, MSE, risk assessment, medications and changes, assessment with coded diagnoses, and a plan with follow-up — and you edit it in plain language.
From a note you already like. "Talk to Template" turns a spoken or typed description into a template; "Start from Sample Note" reverse-engineers the headers and instructions from a de-identified note you paste. Either takes minutes. DAP, BIRP, GIRP, a psychiatric evaluation, a controlled-substance follow-up — all are expressible this way; none needs to be "supported" as a format.
From other psychiatrists. The Network Template Gallery lists templates that real clinicians chose to share — medication-management notes, comprehensive psychiatric evaluations, deprescribing-focused SOAP notes — each with a public preview page and a one-click download into your account.
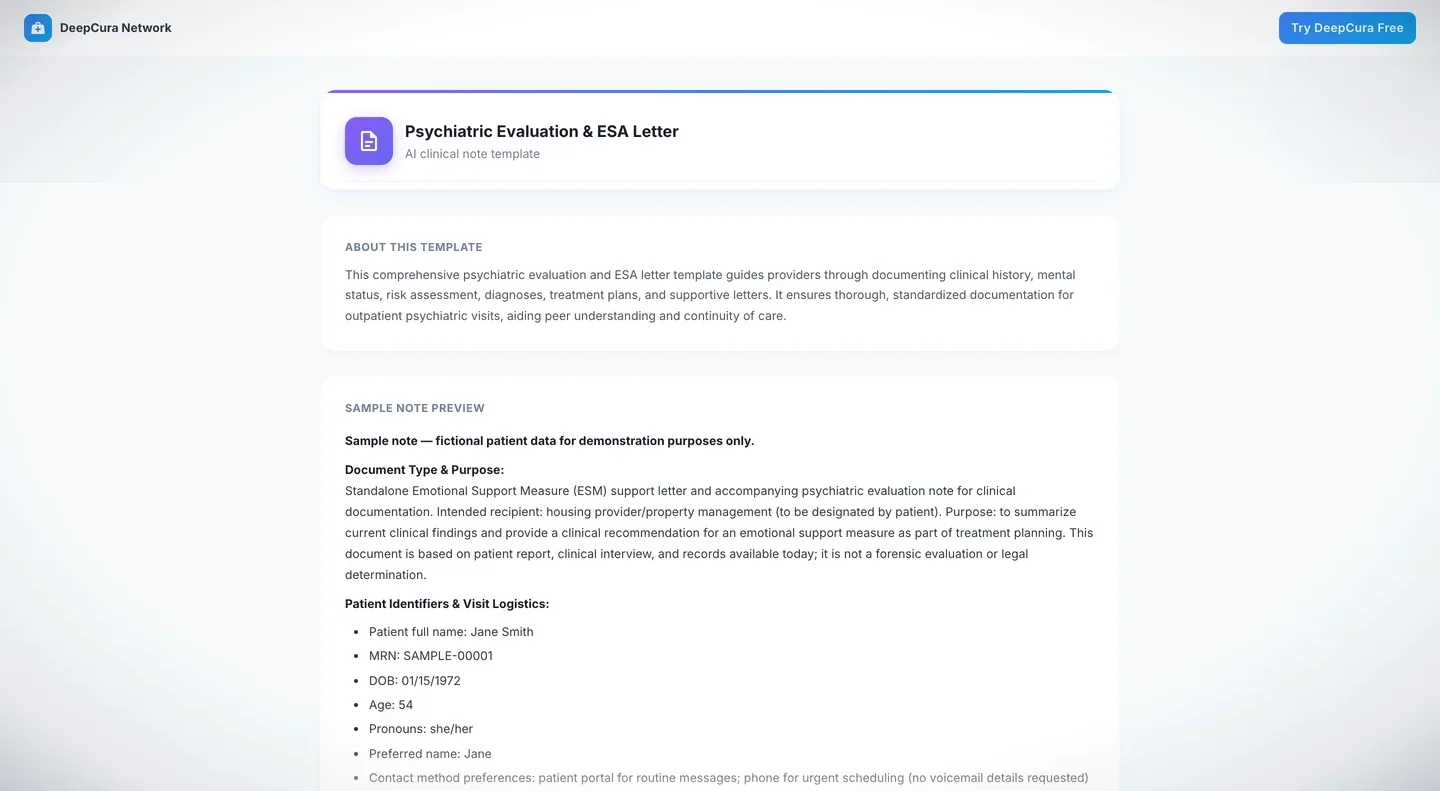
Repeated MSE normals, safety-plan language and consent statements become macros ("Quick Phrases") so the model does not have to reinvent them.
What a DeepCura psychiatry note looks like — and where every line came from

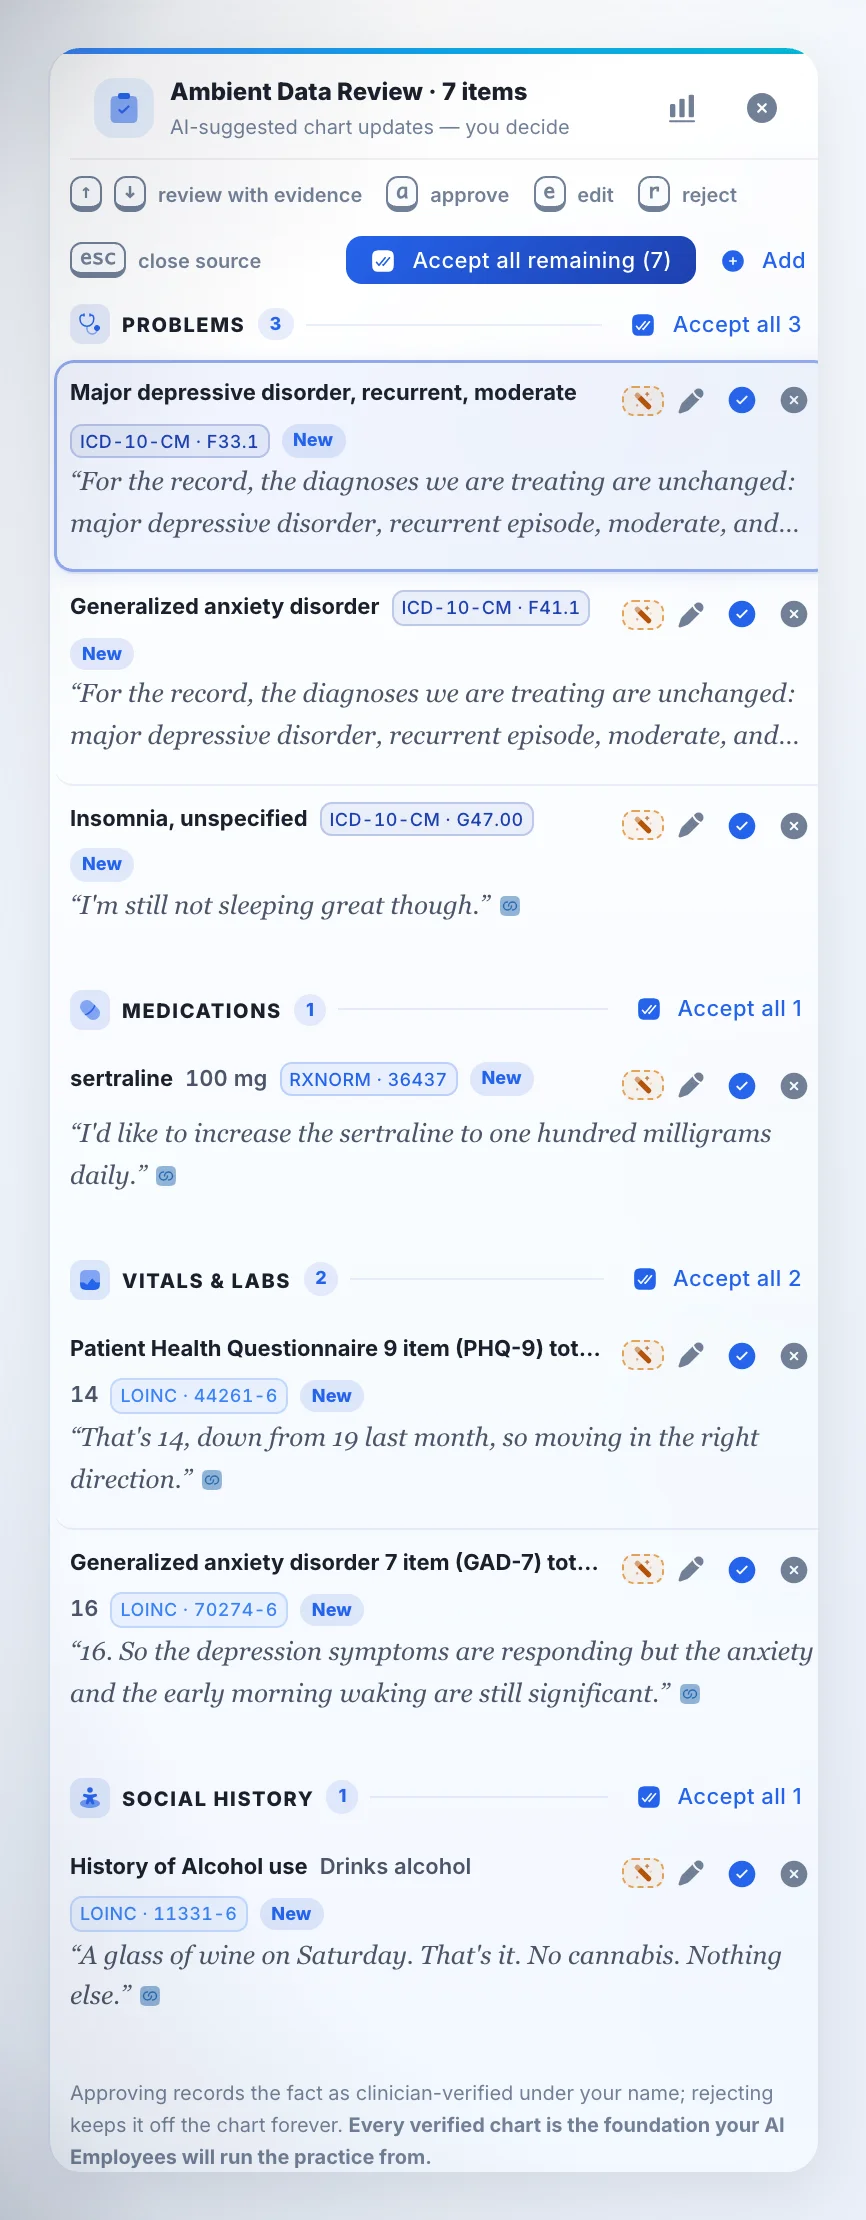
Two things distinguish the note beyond its sections. First, the coded facts inside it — diagnoses, medications, screener scores, substance-use history — are extracted with their codes (ICD-10-CM, RxNorm, LOINC; SNOMED where the EHR requires it) and arrive in an Ambient Data Review queue marked New, as suggestions: nothing enters the chart until you approve, edit or reject each one, and approving records the fact as clinician-verified under your name. Second, each suggestion carries the verbatim phrase it came from, linked back to that moment in the visit transcript — so a PHQ-9 of 14 stated aloud is a value you can trace, trend across visits, and defend, not a number that appeared in a paragraph.
What lands in your EHR: eClinicalWorks, athenaOne, AdvancedMD, OptiMantra, DrChrono
This is the section a documentation-only vendor cannot write. Each EHR receives the note differently; here is what actually happens, per system, and what does not.
eClinicalWorks — Scribe It, with provider-only reasoning
DeepCura converts the finished note into eCW's Scribe It paste format, which the eCW parser files into structured fields. Diagnoses go in as ICD F33.1 - Major depressive disorder, recurrent, moderate: lines, with the exact official ICD-10-CM descriptor — eCW validates the descriptor and silently drops a line that deviates, so DeepCura resolves each one against the NLM ICD-10-CM database rather than paraphrasing. Billing lines go in as Add EM 99214 and Add CPT 90833. Orders go in as per-diagnosis Order lines that link each lab to the diagnosis that justifies it. And the two note fields with different visibility are used deliberately: Treatment notes: is patient-facing (care plan, medication instructions, follow-up), Clinical Notes: is provider-only — where a mental-health practice on eCW we work with routes eating-disorder weight detail and differentials so they never surface in the portal. This is a paste-based integration on the note side (plus FHIR-based scheduling and prechart); the guide to it is here.
athenaOne — MSE into Physical Exam, risk into Assessment, F-codes as SNOMED
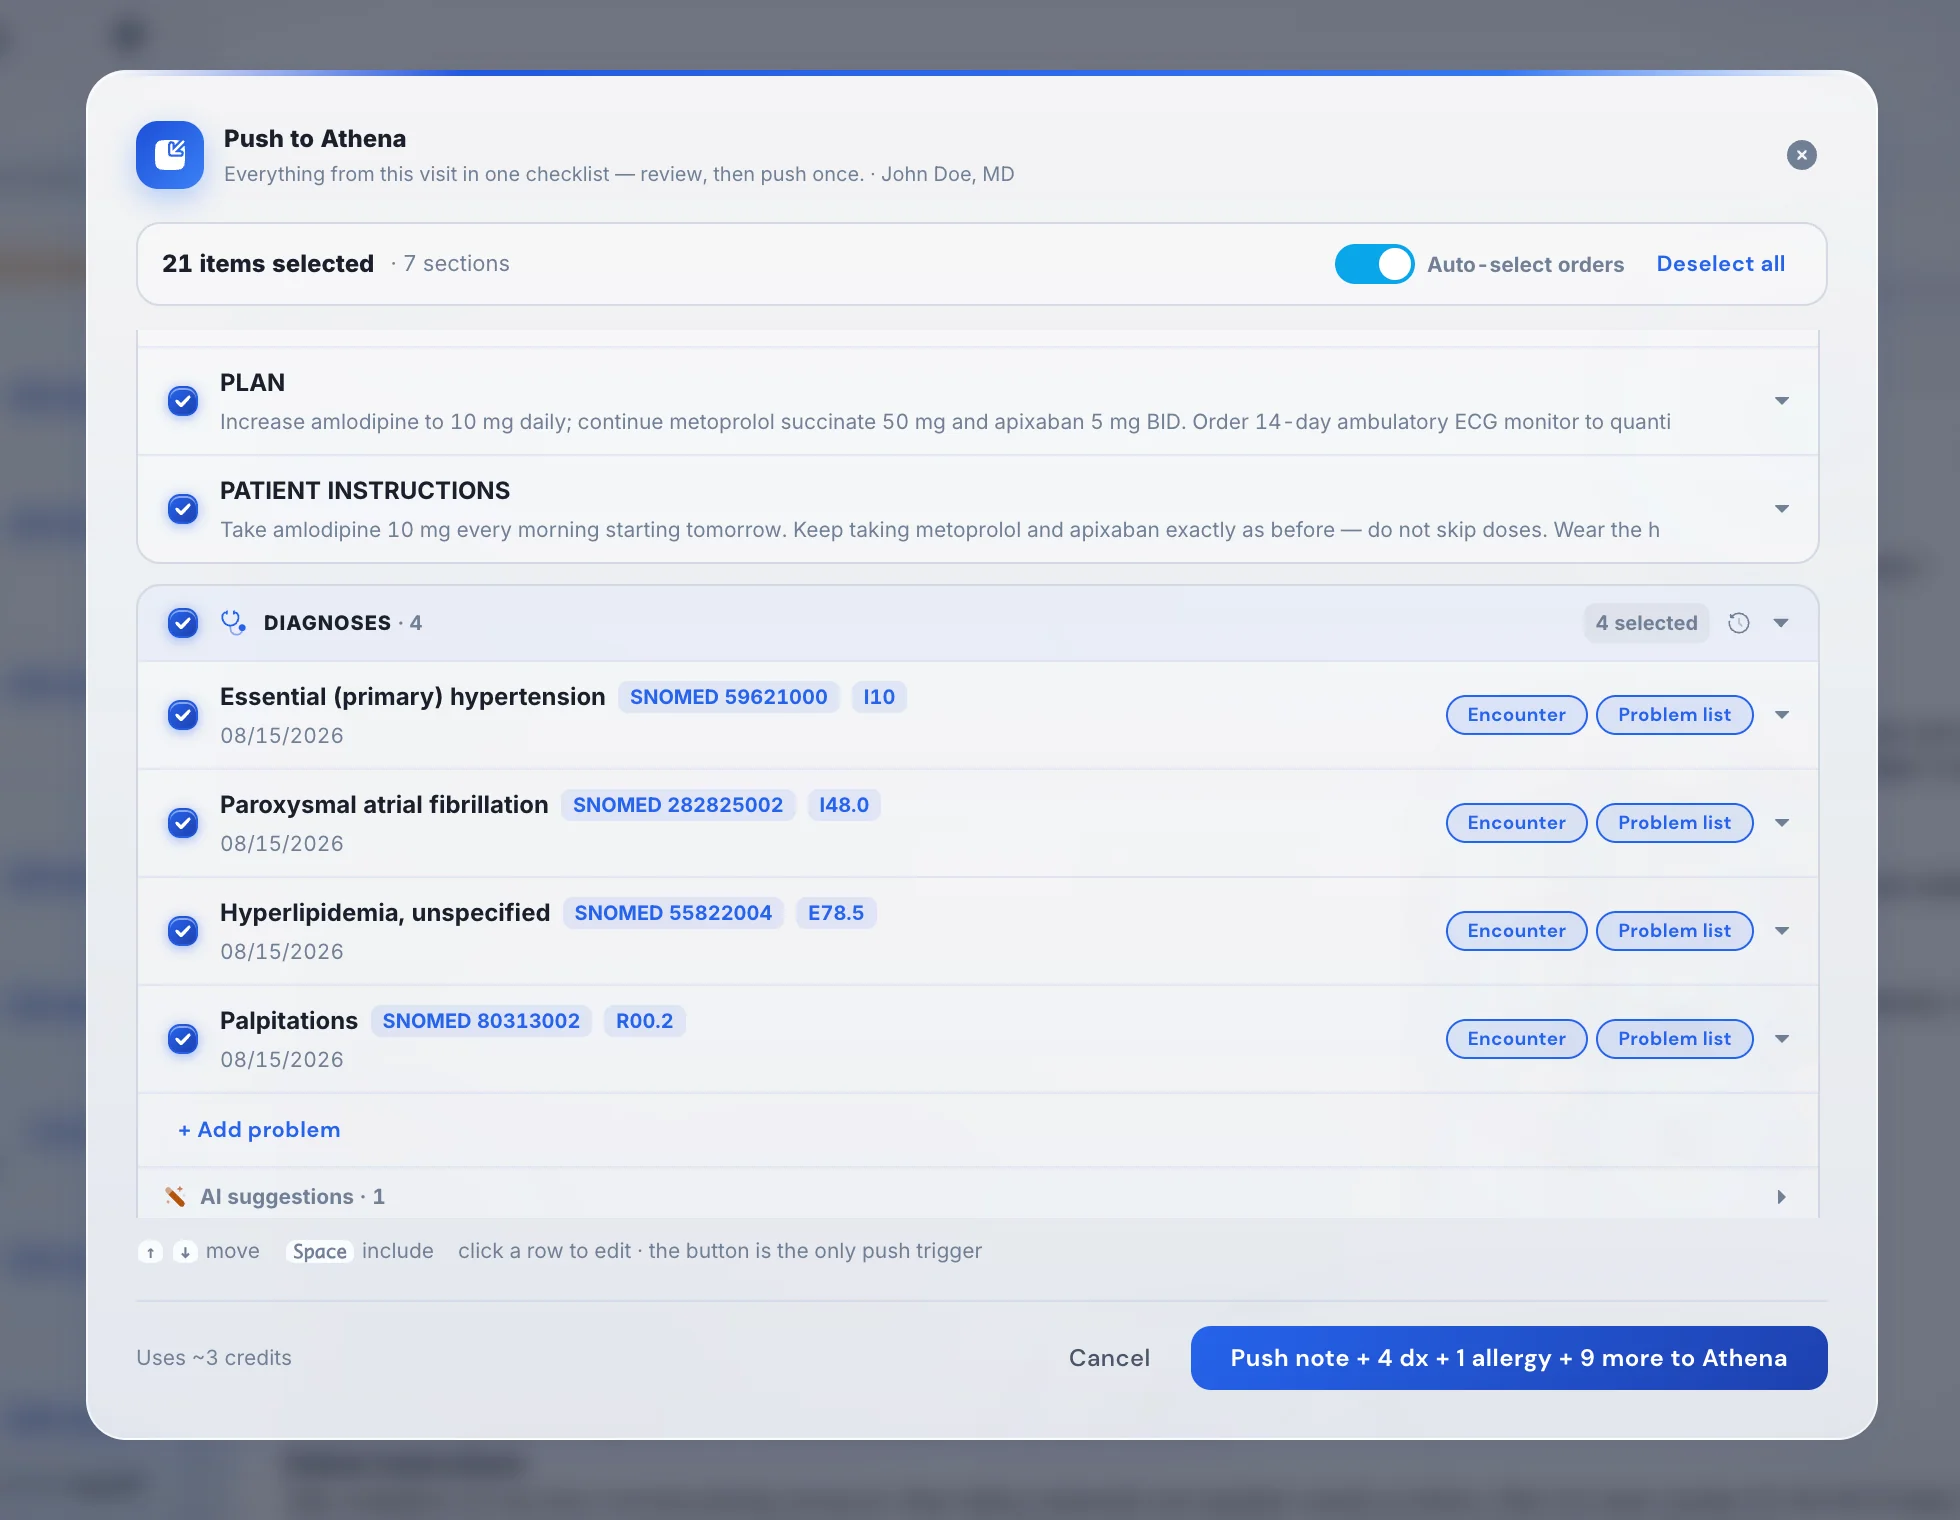
For athenahealth the note is routed section-by-section into athenaOne's encounter fields. Two routings matter for psychiatry: the Mental Status Exam is written into the Physical Exam field as a labeled block (athena has no MSE field), and the Risk / Safety Assessment goes into the Assessment field together with the full assessment-and-plan text. Diagnoses are cross-walked from ICD-10 to the SNOMED concepts athena requires and placed in the encounter's A/P boxes and the problem list; medication orders are matched to athena's own catalog, and the modal flags a strength mismatch between what was dictated and the matched catalog item before anything is sent. Pushing sections costs 0.5 credit each; the note text itself pushes free. If you are on athena and want basic ambient notes with nothing else, athenaAmbient is included in your athenaOne subscription — try it first. The full guide is here.
AdvancedMD — into the psychiatry template your practice already charts on
DeepCura writes into the practice's own AdvancedMD note template — a psychiatry note's HPI, past history, ROS, MSE, risk and A&P controls, whatever your template calls them — and sends only the fields it has content for. That detail matters: a blank field written into AdvancedMD overwrites intake carry-forward and can trigger the template's default option values, so DeepCura never sends blanks. If a same-day note already exists (because your MA opened it in AMD to keep carry-forward intact), the push modal offers "Update today's note" and revises that note in place instead of creating a duplicate. Each AdvancedMD note push costs 0.5 credit. Guide here.
OptiMantra — the AI charting integration OptiMantra offers its practices
OptiMantra lists DeepCura as an AI charting integration its practices can add, with a partner offer for practices that sign up through OptiMantra and published customer case studies [11]. Once connected, when a note is generated — or, with auto-publish off, when you click Push after previewing — DeepCura publishes it into OptiMantra's four charting fields through OptiMantra's DeepCura endpoint. You map your template's sections once in the field mapper: a psychiatry template's MSE typically goes to Objective, the interval history and psychiatric history to Subjective, the coded diagnoses to Assessment and the plan to Plan; the patient name and visit date travel with the note. Turn on auto-publish and every generated note lands in OptiMantra without a click. What the connection does not do: it does not pull OptiMantra's schedule into DeepCura, and orders and prescriptions are not sent through it — those stay in OptiMantra.
DrChrono, Practice Fusion, CharmHealth, Epic — and the EHRs psychiatry actually uses
DrChrono receives the whole note into the clinical-note field you choose on your DrChrono template, per appointment — one field, not sectioned. Practice Fusion is a two-click browser workflow rather than a write-back. And to be plain about the behavioral-health EHRs many psychiatric practices run: Valant, Osmind, SimplePractice, TherapyNotes and Kareo/Tebra have no native DeepCura write-back today — you copy the note in. If that is your EHR and you do not want the phones, inbox and scheduling parts of DeepCura, Freed's browser push into those systems is a legitimate reason to choose Freed.
Coding a psychiatry visit: E&M, the psychotherapy add-on, screeners, F-codes
After the note, the coding step proposes an E&M level from the documented time and medical decision-making, plus the procedure and add-on codes the transcript supports — the psychotherapy add-on when therapy time and content are documented separately, 96127 when a screener was administered and scored. On eClinicalWorks, suggestions are resolved against the ICD-10/CPT library you import (your own descriptors, ordered the way you bill); elsewhere the coder proposes codes from the documentation. Nothing is sent to the EHR until you approve it. Diagnoses come out with ICD-10 specificity — severity, episode, remission status — and link to the same F-codes we document elsewhere on this site, e.g. F41.9 and F32.9. The template built for you includes the MDM and time prompts that make the add-on defensible; the scribe is instructed not to invent time that was not documented — and you should not either.
What a psychiatry day costs in credits (the honest math)
DeepCura's plan is $129 per provider per month with 1,000 credits a month across every AI agent — there is no "unlimited" tier. A standard note costs 1 credit; recording costs 0.1 credit at start and 0.1 per three-minute auto-save; premium reasoning models cost 3 credits per note and the deepest tier 15; pushing sections to athena costs 0.5 credit each (an AdvancedMD note push likewise 0.5). Here is what that means for a psychiatry day:
| Visit | Standard-model cost | With a premium model |
|---|---|---|
| 20-min medication check | ≈ 1.7 credits (1 note + 0.1 start + ~6 auto-saves) | ≈ 3.7 |
| 50-min psychotherapy + E&M | ≈ 2.7 credits | ≈ 4.7 |
| 60-min new-patient evaluation | ≈ 3.1 credits | ≈ 5.1 |
Fifteen medication checks a day, 22 days a month ≈ 330 visits ≈ 560 credits — comfortably inside 1,000. A therapy-heavy day (six 50-minute sessions plus four med checks) ≈ 23 credits/day ≈ 500/month. Run a premium model on every note and you land near 1,200/month, which is what the $59/month add-on (raises the allotment from 1,000 to 2,000 credits) is for; a 40-plus-visits-a-day psychiatric NP needs it. Annual billing is $999 per provider; multi-provider practices pay $116 per seat at 3–5 seats, $110 at 6–10, $101 at 11+; the free trial includes credits and asks for no card. Full pricing is on the plans page.
Which AI scribe fits which psychiatry practice
How we judged. Six psychiatry-specific criteria, weighted: MSE and risk documentation as discrete sections (25%) · E&M plus psychotherapy add-on coding support (15%) · portal-sensitive routing, i.e. a provider-only field (10%) · write-back into the EHRs psychiatric practices use (20%) · medication-management and controlled-substance note quality (15%) · price per note at 300 visits a month (15%). Evidence: for DeepCura, the shipping product and the captures on this page; for other vendors, their published documentation and pricing as of the dates shown in the pricing table. We have not run a controlled head-to-head note-quality trial across all vendors, so we publish a fit table rather than numeric scores.
| Practice situation | Strongest fit | Why | Trade-off |
|---|---|---|---|
| Independent psychiatry / PMHNP on eCW, athenaOne, AdvancedMD, OptiMantra or DrChrono | DeepCura | Note built to your template; MSE/risk routed into real EHR fields; add-on coding; phones, inbox and scheduling in the same account | Credits, not unlimited; templates are built, not picked from a list; more product to learn |
| Behavioral-health-only documentation, part-time caseload | JotPsych | Sections and pricing built around psychiatry alone; a 15-notes-a-month plan for moonlighting | EHR path is a browser extension add-on; no phones/inbox |
| Browser EHR DeepCura does not write into (SimplePractice, TherapyNotes, Valant, Osmind) | Freed AI | Least setup; browser push on the Premier plan | MSE/risk sections depend on your template; per-note limits on Starter |
| Multilingual sessions or "let me try it free first" | Heidi Health | Free tier; multilingual capture | Clinician plan is $150/mo month-to-month (less billed annually); limited US write-back depth |
| Health-system psychiatry on Epic / Cerner | Nuance DAX / Dragon Copilot | Enterprise EHR embedding and procurement | Enterprise pricing, not published; overkill for a private practice |
| Voice-command charting inside athena / Epic / Cerner / MEDITECH | Suki | Dictate-and-structure workflow | Pricing not published; documentation-focused |
| athenaOne user who only wants basic ambient notes | athenaAmbient | Included in athenaOne | Basic; no add-on coding depth, no phones |
| Budget-first solo practice that wants a template menu to pick from | S10.AI | Large pre-built template menu incl. psychiatric evaluation and intake formats; $199/mo Solo, $159/mo per provider Practice | Template-based rather than built to your note; documentation-focused |
| Tool | Plans | Monthly | Included / limits | Verified |
|---|---|---|---|---|
| DeepCura | All AI agents, per provider | $129 ($83.25 billed annually) | 1,000 credits/mo; 1 credit per standard note; +$59/mo add-on raises it to 2,000; seat tiers from $101 | 2026-08-17 |
| JotPsych | Moonlighting · Basic · Everything · EHR Extension add-on | $53 · $135 · $269 · $8 | 15 notes/mo · unlimited notes · push notes to your system | 2026-08-17 |
| Freed AI | Starter · Core · Premier | $39 · $79 · $119 ($104 billed annually) | 40 notes/mo · unlimited notes · EHR push + ICD-10/CPT; 7-day trial | 2026-09-27 |
| Heidi Health | Free · Clinician | Free · $150 ($110 billed annually) | unlimited transcription + standard templates; advanced features gated · per user; 14-day free trial; custom templates | 2026-09-27 |
| S10.AI | Solo · Practice | $199 · $159 | per provider · includes BRAVO receptionist (1,000 calls) | 2026-08-17 |
| Suki AI | Not published (pricing page unavailable); reported ~$299/user/mo — contact sales | not published | Not published (pricing page unavailable); reported ~$299/user/mo — contact sales | 2026-08-17 |
| Nuance DAX / Dragon Copilot | Enterprise contract; not publicly priced | not published | Enterprise contract; not publicly priced | 2026-08-17 |
| athenaAmbient (athenaOne) | Included for athenaOne customers | Free | basic ambient notes inside athenaOne | 2026-03-20 |
Vendor prices verified on the dates shown (earliest 2026-03-20); vendors change plans — confirm with each vendor before buying. DeepCura row: current plan; competitor rows: publicly published prices.
Where DeepCura is not the right pick. A therapy-only practice that will never prescribe (Mentalyc and Upheal are built for that — our Mentalyc review); a group that needs a dedicated group-therapy workflow (DeepCura transcribes multiple speakers, but there is no purpose-built group note); an academic department that must have every note in Epic through an enterprise contract; a solo clinician on Valant or Osmind who wants zero copy-paste. DeepCura's own limitations, plainly: no shipped template library (five minutes to build one), credits rather than an uncapped note allowance, premium models cost 3–15 credits, and the breadth of the platform means a learning curve a documentation-only tool does not have.
For the site-wide comparison of fifteen scribes with the full scoring method, see the best AI medical scribes ranking; for the two most common alternatives in depth, the Freed AI review and the Heidi Health review.
Beyond the note: the intake calls, the schedule, the inbox
The same account that writes the note answers the new-patient intake calls (an AI receptionist with an included phone number), books and reminds, and works the fax, email and SMS queue from one inbox — with every action previewed and confirmed by you. That is why DeepCura describes itself as an Electronic Health Workforce rather than a scribe: the EHR keeps the record; the workforce does the work around it. If your bottleneck is the phone rather than the note, start with the AI receptionist guide.
Talk to Emily, DeepCura's onboarding agent
She builds your psychiatry template on the call. $129/mo · 1,000 credits/mo · free trial, no card.
+1 (415) 549-1829Available 24/7 · Set up in seconds · No credit card required
Psychiatric clinicians on record

I have a one on one conversation with them. We look each other in the eyes. I let them know that I am listening to them. It's been a massive help for me in my practice.
On Reddit's r/PMHNP, clinicians describing a switch to DeepCura cite direct EHR integration and minimal edit time; we collect those threads in the Reddit guide. DeepCura also completed the American Psychiatric Association's Committee on Mental Health Information Technology vendor inquiry, published on psychiatry.org — a questionnaire, not an endorsement or rating.
Privacy for psychiatric records: BAA, recordings, 42 CFR Part 2, consent
Every DeepCura customer is covered by a Business Associate Agreement; PHI is encrypted in transit and at rest; your data is not used to train models. Recordings and transcripts stay in your account so that every chart fact can replay the moment it was said — that traceability is a feature; you can remove any transcript from your workspace, and account-level deletion requests are handled under the BAA (see the Trust Center). DeepCura does not claim 42 CFR Part 2 program compliance: a Part 2 program must evaluate its own consent and segmentation obligations under the 2024 final rule, which took effect for compliance in February 2026, before recording SUD encounters with any scribe. Recording consent follows your state's law (two-party-consent states require the patient's agreement on the record — a one-line Quick Phrase documents that agreement in every note). Telehealth visits work alongside whichever video platform you use.
Frequently Asked Questions
What is the best AI scribe for psychiatry?
It depends on the practice. For an independent psychiatry or PMHNP practice on eClinicalWorks, athenaOne, AdvancedMD, OptiMantra or DrChrono, DeepCura is the strongest fit because the note is built to your template and written into those systems' fields. JotPsych fits behavioral-health-only documentation and part-time volume; Freed fits browser EHRs DeepCura does not write into; Heidi fits multilingual sessions; DAX or Suki fit health-system psychiatry on Epic or Cerner.
Does an AI scribe write the mental status exam?
DeepCura writes the MSE as labeled fields when the template you build asks for them, and routes it into the right place per EHR — a labeled block inside athenaOne's Physical Exam field, the MSE control on your own AdvancedMD template, or OptiMantra's Objective field when your template keeps the MSE in the objective section. General-purpose scribes usually leave MSE observations inside the HPI narrative.
Can it code the psychotherapy add-on (90833, 90836, 90838) and 96127?
It proposes the E&M level from documented time and medical decision-making and adds the procedure and add-on codes the transcript supports (on eClinicalWorks, resolved against the code library you import). You approve every code before it is sent. The add-on still requires therapy time and content documented separately from the medical management — the template prompts for that.
Is Freed AI good for psychiatry?
Freed is the simplest ambient scribe and its Premier plan ($119/month, $104 billed annually) pushes notes into browser-based EHRs, which makes it a fair choice for a psychiatrist on SimplePractice, TherapyNotes, Valant or Osmind. Its default note is SOAP-style — MSE and risk sections depend on the template you configure — and it does not handle phones, inbox or scheduling.
Is Heidi Health good for psychiatry?
Heidi is a good fit for multilingual sessions and offers a free tier to try; the Clinician plan is $150 per user per month on monthly billing, less billed annually. Its US EHR write-back depth is limited compared with the field-level routing described above.
Is JotPsych better than DeepCura for psychiatry?
For documentation-only behavioral-health depth — and for part-time clinicians who want a 15-notes-a-month plan — JotPsych is a strong choice ($53, $135 or $269 per month, plus an $8 EHR extension). DeepCura is the better fit when you want the note written into your EHR's fields and the phones, inbox and scheduling handled in the same account for $129 per month.
Is it HIPAA compliant, and what about 42 CFR Part 2 and recordings?
Yes to HIPAA: BAA with every customer, encryption in transit and at rest, no model training on your data. Recordings and transcripts remain in your account for evidence traceability; you can remove a transcript from your workspace, and account-level deletion requests are handled under the BAA. DeepCura does not claim 42 CFR Part 2 program compliance; Part 2 programs must evaluate their own consent and segmentation obligations.
Can it document controlled-substance and medication-management visits?
Yes — the template built for your account prompts for medication reconciliation, side-effect screening, dose-change rationale, the PDMP check, informed consent and the refill interval, and the note is generated from what was said in the visit.
Which EHRs does it write into for psychiatry — and which not?
Native write-back today: athenahealth, eClinicalWorks (Scribe It paste plus FHIR scheduling), AdvancedMD, OptiMantra, Epic, DrChrono, CharmHealth and Cerner. No native write-back for Valant, Osmind, SimplePractice, TherapyNotes or Kareo/Tebra — you copy the note into those.
What does it cost per note?
$129 per provider per month includes 1,000 credits; a standard note is 1 credit, recording adds 0.1 credit at start and per three-minute auto-save, premium reasoning models cost 3 credits and the deepest tier 15. A 20-minute medication check comes to about 1.7 credits; 15 such visits a day for 22 days is about 560 credits a month. An extra 1,000 credits costs $59 per month; annual billing is $999 per provider.
References
[1] Centers for Medicare & Medicaid Services / AMA, "Evaluation and Management Services — 2021 office/outpatient E/M guidelines (MDM and time)." cms.gov
[2] Office of the National Coordinator for Health IT, "Information Blocking — 21st Century Cures Act Final Rule." healthit.gov
[3] SAMHSA, "Confidentiality of Substance Use Disorder Patient Records — 42 CFR Part 2 Final Rule (February 2024; compliance date February 16, 2026)." samhsa.gov
[4] Posner K, et al. "The Columbia–Suicide Severity Rating Scale." American Journal of Psychiatry 168(12), 2011. cssrs.columbia.edu
[5] Kroenke K, Spitzer RL, Williams JB. "The PHQ-9: validity of a brief depression severity measure." J Gen Intern Med 16(9), 2001; Spitzer RL, et al. "A brief measure for assessing generalized anxiety disorder: the GAD-7." Arch Intern Med 166(10), 2006.
[6] American Psychiatric Association, "Practice Guidelines for the Psychiatric Evaluation of Adults," 3rd ed. psychiatry.org
[7] American Psychiatric Association Committee on Mental Health Information Technology, "DeepCura — vendor inquiry" (PDF). psychiatry.org
[8] Vendor pricing pages, accessed 2026-08-17: getfreed.ai/pricing (Freed AI); jotpsych.com/pricing (JotPsych); s10.ai/pricing (S10.AI); Heidi Health Clinician plan as documented in our Heidi Health review (updated 2026-08-03); Suki and Nuance/Dragon Copilot pricing not publicly listed.
[9] DeepCura, "Plans & Pricing" and Trust Center. deepcura.com/plans-pricing · trust.deepcura.com
[10] Justin, Psychiatric Nurse Practitioner — video testimonial. youtube.com/shorts/xkvaubw1NP8
[11] OptiMantra, "Case study: how Optimal Body Health streamlined patient care with DeepCura + OptiMantra." optimantra.com